A sore throat every few months does not automatically mean repeated bacterial tonsillitis, but a pattern of frequent, severe, prolonged or poorly explained symptoms deserves closer review. By tracking each episode and recognising urgent warning signs, you can decide whether to monitor at home, seek prompt medical care or arrange an ENT examination.
Key takeaways
- Count separate illnesses only after you have fully recovered between episodes.
- Reflux, allergies, dry air and mouth breathing can mimic repeated throat infections.
- Seek urgent care for breathing difficulty, drooling, severe swelling or inability to swallow.
- Children need assessment based on growth, sleep, feeding and repeated infections—not symptoms alone.
When Does a Throat Problem Count as Recurring?
Recurring throat problems mean separate illnesses after complete recovery, not one infection that never clears. Persistent irritation from reflux, allergy, dry air or mouth breathing can mimic a recurrent sore throat without causing distinct infections.
| Pattern | What it means | Clues |
|---|---|---|
| Separate episodes | New illness after recovery | Symptoms return after a symptom-free interval |
| Unresolved infection | One illness has not fully settled | Continuous fever, pain or swelling without recovery |
| Persistent irritation | Ongoing inflammation without repeated infection | Repeated throat clearing, dryness or symptoms linked to meals, seasons or voice use |
Use the commonly used Paradise criteria as a practical threshold for assessment: at least 7 documented episodes in one year, 5 episodes per year for two consecutive years, or 3 episodes per year for three consecutive years.
Each counted episode needs a supporting feature—fever, enlarged neck glands, tonsillar exudate or a positive group A streptococcal test—plus appropriate treatment and clinical documentation.
Keep a throat symptom diary. For every episode, record the date, temperature, tonsil swelling or exudate, cough, swallowing pain, missed school or work, antibiotics taken, test results and recovery date.
Children below these thresholds usually receive watchful waiting rather than immediate tonsil surgery. The decision changes with antibiotic intolerance, periodic fever with aphthous ulcers and adenitis, or a previous peritonsillar abscess. Persistent symptoms between episodes also deserve examination because they may reflect irritation rather than infection.
How Can You Tell Infection from Reflux, Allergy or Irritation?
Repeated sore throats do not automatically mean recurrent bacterial tonsillitis. A viral sore throat is more likely when you have cough, runny nose, hoarseness, oral ulcers or conjunctivitis. Fever, painful swallowing, tonsillar exudate and tender neck nodes fit streptococcal pharyngitis, but they still require clinical assessment rather than assumption.
Other causes include allergy-related post-nasal drainage, acid reflux, dry air, mouth breathing, smoke or chemical irritants and voice overuse. These often produce throat clearing, globus, morning soreness or hoarseness without a bacterial infection.
Use this checklist when symptoms return:
- Seek assessment for suspected group A streptococcal infection; a clinician may use a rapid antigen detection test or throat swab.
- For a symptomatic child aged 3 years or older, arrange a throat culture after a negative rapid test. Routine backup culture is not usually required for adults.
- Do not start antibiotics for every sore throat. Unnecessary treatment causes side effects and promotes resistance; leftover medicine and incomplete courses can leave the wrong drug, dose or duration to guide future treatment.
- Do not automatically self-medicate with steroids, antiseptic gargles or reflux medicines. Each needs clinician-directed use because the treatment depends on the cause and your medical history.
- Note triggers: dust, meals, lying down, dry rooms, nasal blockage and prolonged speaking. A pattern often separates irritation or reflux from infection.
Contact an ENT clinician when symptoms persist, recur without clear recovery, or keep prompting medication. Examination can identify drainage, reflux-related irritation, tonsil disease or another throat problem.
Which Throat Symptoms Need Urgent Care?
Difficulty breathing, stridor, inability to swallow liquids or saliva, drooling, dehydration, rapidly worsening symptoms, neck swelling, or severe difficulty opening your mouth require immediate medical help. Do not wait for a routine ENT appointment.
| Seek emergency care now | Arrange prompt medical review |
|---|---|
| Difficulty breathing or stridor | Persistent one-sided sore throat |
| Inability to swallow liquids or saliva, or drooling | Progressive difficulty swallowing or pain on swallowing |
| Rapidly worsening throat symptoms or dehydration | Unexplained neck swelling |
| One-sided throat swelling, severe trismus, or a hot-potato voice | A lump or ulcer in the mouth or throat |
| Neck swelling or suspected airway emergency | Referred ear pain without an ear cause |
Severe one-sided pain, uvula deviation away from the affected side, trismus, drooling, and a hot-potato voice can indicate a peritonsillar abscess. This infection needs urgent assessment because swelling can threaten the airway.
Drooling and breathing difficulty can signal a dangerous supraglottic infection, including epiglottitis. Keep the person calm and upright, seek emergency help, and do not repeatedly probe the throat with a tongue depressor; stimulation can worsen airway obstruction.
Persistent unilateral symptoms, a lump, ulcer, progressive swallowing trouble, or referred ear pain also need prompt examination because serious head-and-neck disease can present this way.
How Do Children and Adults Need Different Assessment?
Age changes the assessment pathway: children are assessed for both children and recurrent throat infections and airway obstruction, while adults need closer attention to persistent irritation and laryngeal or head-and-neck disease.
For a child with enlarged tonsils or adenoids, ask about:
- Loud snoring or snoring and sleep apnea
- Restless sleep
- Witnessed breathing pauses
- Morning headaches
- Daytime sleepiness
- Irritability
- Poor school performance
These signs suggest obstructive sleep-disordered breathing, not simply frequent infection. A child with obstructive sleep apnea and tonsil or adenoid enlargement may need a sleep assessment and treatment discussion even when infection frequency is below tonsillectomy thresholds. Persistent symptoms after tonsil or adenoid surgery need reassessment.
In adults, recurring throat symptoms often connect with reflux, allergy, smoking, alcohol exposure, heavy voice use or mouth breathing. Persistent hoarseness or dysphonia beyond four weeks needs laryngeal examination rather than repeated empiric treatment. A persistent neck lump, unilateral throat pain or referred ear pain also warrants examination, particularly when home treatments keep failing.
Tonsil stones are different from acute tonsillitis. Small, symptom-free tonsil stones usually need oral hygiene and reassurance. Arrange an ENT examination for painful, bleeding or troublesome tonsil stones, or when the diagnosis is uncertain.
What Happens During an ENT Examination?
Bring your episode record, medication list and test results to an ENT examination. The clinician uses them to decide whether repeated symptoms reflect infection, post-nasal drainage, reflux, obstruction or a laryngeal problem.
1. Expect questions about episode dates, fever pattern, antibiotics and other medicines, recovery, swallowing pain, breathing difficulty, sleep quality, snoring, allergy or reflux symptoms, and voice changes.
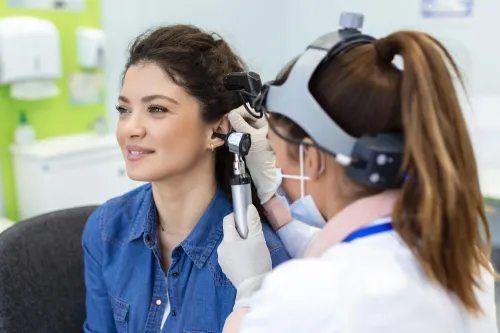
2. The throat examination includes inspection of the mouth, tongue, throat and tonsils. The clinician also feels the neck for tender or enlarged lymph nodes, examines the nose, and assesses your voice and swallowing.
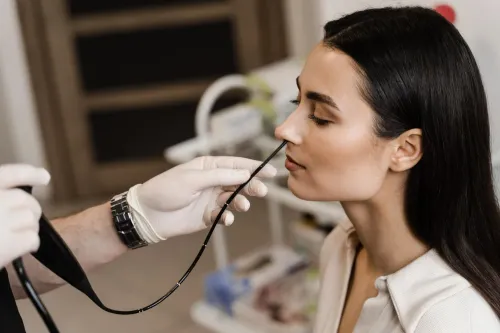
3. If symptoms suggest disease in the nose, nasopharynx, larynx or vocal folds, flexible nasendoscopy can provide a direct view through the nose. This form of laryngoscopy can reveal inflammation, vocal-fold lesions or impaired movement that symptoms alone cannot distinguish.
4. Blood tests are usually reserved for suspected systemic illness rather than every recurring sore throat. For hoarseness, CT or MRI is usually unnecessary before the larynx has been visualised; persistent dysphonia beyond four weeks needs laryngeal examination.
5. The findings show whether surgery is relevant, or whether treatment should target drainage, reflux, allergy, obstruction or voice use instead. Dr.Phadke’s ENT & Rhinoplasty Clinic-08048038595 can help a Pune patient organise that assessment around documented symptoms, examination findings and appropriate testing rather than repeated self-treatment.
Related service
Best Tonsil and Adenoid Surgeon in Bavdhan, Kothrud, Pune, PCMC If you or your child is suffering from recurrent tonsillitis, enlarged adenoids, breathing difficulties, snoring, or frequent throat infections,... View service → |
Frequently asked questions
When does a throat problem count as recurring?
It counts as recurring when separate throat illnesses happen after you have completely recovered. Ongoing irritation from reflux, allergy, dry air or mouth breathing is not the same as repeated infections.
How can you tell infection from reflux, allergy or irritation?
Fever, swollen neck glands, pus on the tonsils and sudden painful swallowing support infection. Heartburn, sour taste, throat clearing, nasal symptoms, dry air or mouth breathing point toward other causes.
Which throat symptoms need urgent care?
Seek urgent care for breathing difficulty, drooling, inability to swallow liquids, rapidly increasing neck or throat swelling, a muffled voice or severe one-sided throat pain.
How do children and adults need different assessment?
Children need assessment of feeding, growth, sleep, snoring, hearing and school absence alongside throat symptoms. Adults also need review of reflux, smoking, medicines, voice changes and persistent symptoms.
What happens during an ENT examination?
An ENT clinician reviews your episodes, examines the mouth, tonsils, nose, ears and neck, and checks the voice. Further tests depend on findings and may include a throat swab or flexible scope.