Ear symptoms become more concerning when they persist beyond a reasonable recovery period, return after treatment, affect one ear, or come with hearing, balance, drainage or neurological changes. By the end, you will know which symptoms need urgent care, when to book an ENT assessment, what the evaluation includes and how to prepare.
Key takeaways
- Seek review if symptoms persist beyond 48 to 72 hours without clear improvement.
- Ongoing or returning ear drainage needs medical assessment, especially with a perforated eardrum.
- One-sided symptoms, repeated episodes and lasting fluid require closer evaluation.
- Keep objects and unprescribed drops out of the ear while waiting for care.
How long can you wait before persistent ear symptoms need assessment?
Do not keep treating ear symptoms yourself beyond 48 to 72 hours if appropriate care has not clearly helped. Persistent ear pain, blocked hearing, ear fullness, itching or discharge needs reassessment. Use this ear discharge duration rule: ongoing drainage after treatment, or drainage that returns through a perforated eardrum, warrants medical review.
- Seek urgent care for sudden hearing loss that develops over 3 days or less, especially when wax or visible middle-ear disease does not explain it. If onset was within the previous 30 days, arrange referral within 24 hours because treatment can be time-sensitive.
- Seek urgent care for severe or persistent vertigo, facial weakness, swelling or redness behind the ear, a protruding ear, high fever, severe headache, blood or clear fluid from the ear, severe pain, or worsening illness.
- Arrange prompt assessment when fluid or reduced hearing remains after an infection, pain keeps returning, or symptoms continue for several weeks. Persistent discharge, foul smell or worsening hearing should not wait for repeated drops or antibiotics.
- If you have diabetes or immune suppression, obtain earlier review for severe swimmer’s-ear pain, pain out of proportion to examination findings, granulation tissue or persistent drainage. These signs can indicate a serious infection requiring specialist treatment.
Routine ENT evaluation is appropriate for lingering fullness, itching or reduced hearing without emergency signs. Improvement in pain alone does not prove the underlying problem has cleared.
What do repeated ear episodes, one-sided symptoms and lasting fluid indicate?
Count discrete infections, not every day of ear discomfort. Recurrent ear infections means three infections in six months or four infections in twelve months, with one in the preceding six months. Before considering ear tubes, examination must confirm whether middle-ear fluid is present.
1. Symptoms that return after antibiotics, fluid that remains after an infection, or repeated antibiotic courses justify investigation of the underlying cause. The problem could be persistent fluid, Eustachian-tube dysfunction, an eardrum problem or an incorrectly identified infection.
2. Persistent one-sided hearing loss, meaningful hearing asymmetry, unilateral tinnitus or unilateral middle-ear fluid needs formal hearing testing and ENT assessment, especially without a recent cold or allergy. A pure-tone difference of at least 15 dB at two adjacent frequencies can lead to consideration of MRI of the internal auditory canals.
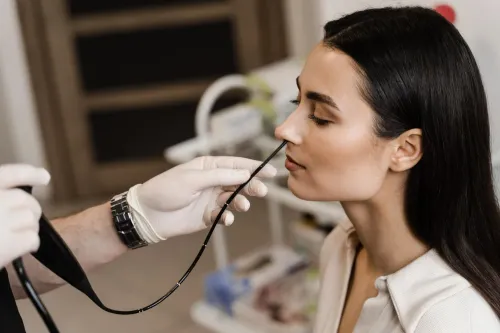
3. Adult unilateral fluid can result from Eustachian-tube obstruction. An ENT assessment may include examination of the nose and throat or nasopharyngoscopy to inspect the area behind the nose.
4. For children with glue ear, hearing assessment and three months of observation often come before tubes. Arrange earlier specialist management when hearing loss is substantial, symptoms are troublesome, or the child has Down syndrome, cleft palate, or speech-and-language problems.
Keep a symptom record with dates, affected ear, treatments and hearing changes. Patterns matter more than labels: repeated “infections” without confirmed fluid can expose you to antibiotics without treating the real cause.
Which symptom patterns point beyond ordinary ear infection?
Record these patterns before your appointment:
- One-sided hearing loss or worsening hearing
- Tinnitus in one ear, especially pulsatile tinnitus matching your heartbeat
- Ear discharge, foul smell or recurrent pain
- Dizziness, imbalance or difficulty understanding speech
| Pattern | What it suggests | Management clue |
|---|---|---|
| Blocked hearing without pain | Earwax blockage | Confirm with an ear examination; remove wax safely |
| Itchy, painful canal after swimming | Swimmer’s ear | Canal treatment; keep water out |
| Pain, fever and reduced hearing | Middle-ear infection | Medical assessment, not repeated self-treatment |
| Fullness, popping after a cold or flight | Eustachian-tube dysfunction | Treat the cause and assess persistent fluid |
| Drainage after a tear in the eardrum | Perforated eardrum | Keep the ear dry and arrange review |
| Recurrent or persistent drainage | Chronic otitis media | Check for chronic suppurative disease |
| Foul-smelling drainage through a perforation | Cholesteatoma symptoms | Prompt ENT assessment; cholesteatoma can damage ossicles without severe pain |
| Gradual hearing loss with ringing | Age- or noise-related loss | Hearing testing and tinnitus assessment |
Brief vertigo triggered by turning in bed can fit BPPV. Positional testing assesses it, and a canalith-repositioning maneuver treats it; persistent spontaneous vertigo, hearing changes or neurological symptoms need a different evaluation.
Pulsatile tinnitus, unilateral tinnitus with asymmetric hearing loss, or tinnitus with vestibular or neurological symptoms lowers the referral threshold. Persistent ear pain with a normal ear exam can arise from the jaw, teeth, throat or neck; swallowing pain, hoarseness, a neck lump, smoking or heavy alcohol use warrants upper-airway and neck examination.
What happens during an ENT evaluation, and how should you prepare?
An ENT evaluation usually moves from your history to ear examination, hearing tests and targeted investigations. The sequence helps separate wax, infection, fluid, perforation, hearing loss and referred pain, because each needs different treatment.
- Describe when symptoms began, how long they last, whether they recur, and what triggers them. Mention previous infections, treatment response and associated discharge, hearing loss, tinnitus, dizziness or pain.
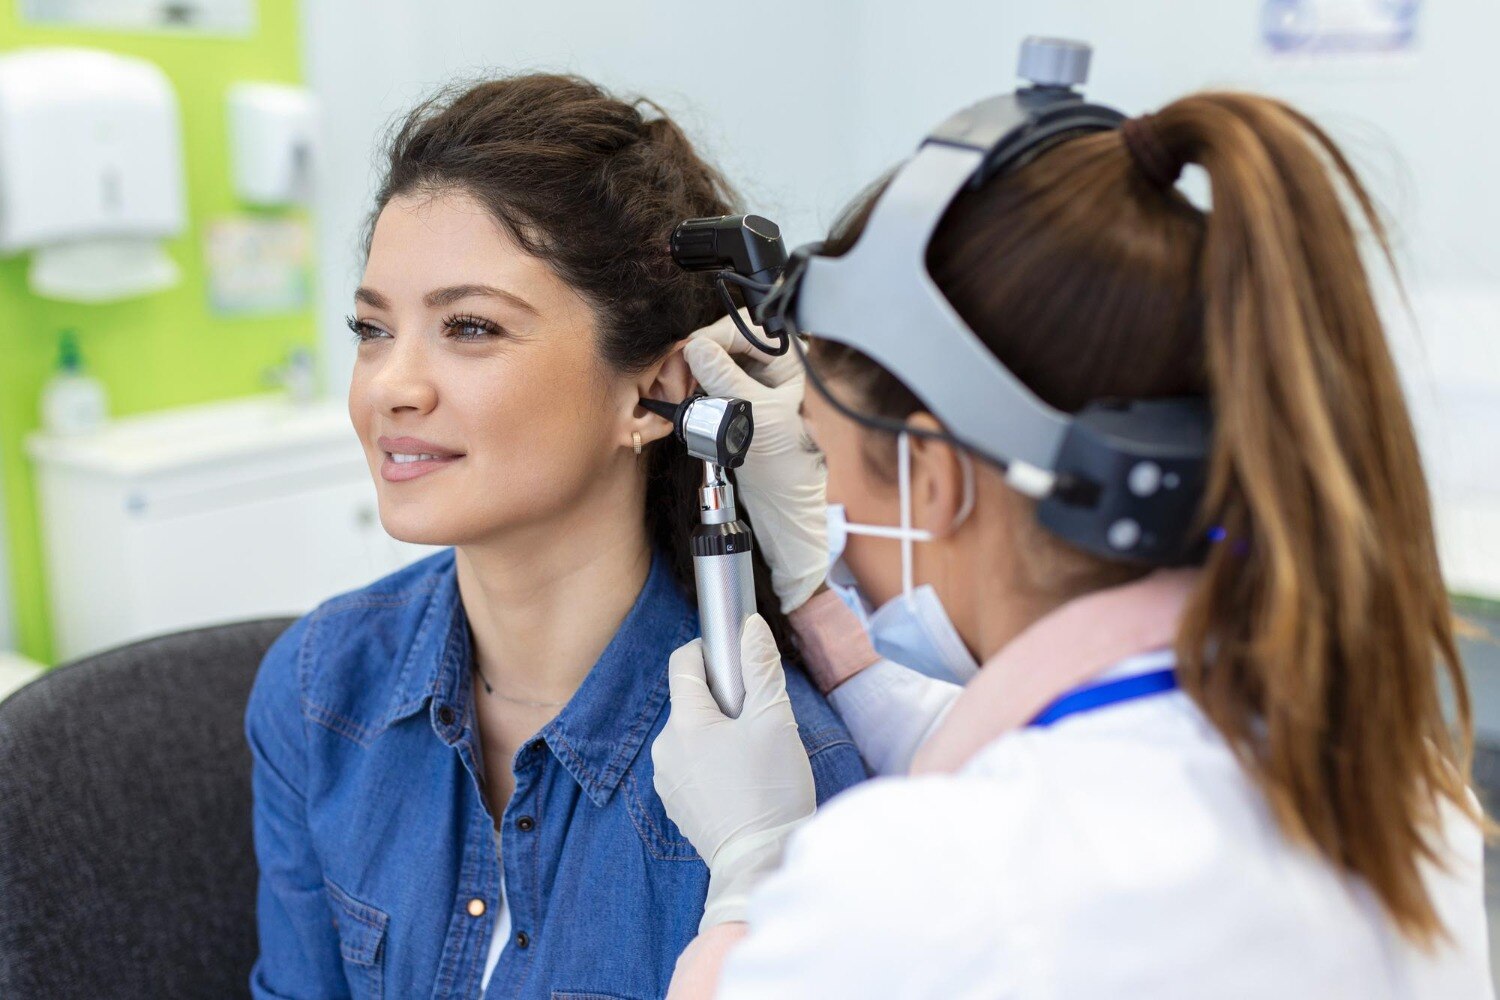
- The clinician performs otoscopy to inspect the ear canal and eardrum. A microscopic ear examination gives a closer view when the canal, eardrum or drainage needs detailed assessment.
- Pure-tone audiometry or another hearing test measures hearing in each ear. Tympanometry checks eardrum movement and middle-ear pressure.
- Findings determine whether you need imaging, vestibular testing, nasopharyngoscopy, or MRI of the internal auditory canals for selected asymmetric sensorineural hearing loss. Adult one-sided middle-ear fluid can prompt a nose-and-throat examination.
Dr.Phadke’s ENT & Rhinoplasty Clinic-08048038595 can assess persistent ear symptoms and match the examination and testing to the suspected cause rather than repeating treatment blindly.
Prepare a short record containing:
- Symptom dates, previous infections, antibiotic and ear-drop names
- Water or loud-noise exposure, flights, trauma and prior ear surgery
- Diabetes, immune suppression and current medicines
- Hearing-test reports and medicine lists
- Whether discharge, hearing loss or dizziness followed treatment
Bring the containers or photographs of prescribed drops when possible. This information can reveal why symptoms returned and prevent an important detail from being missed.
Related service
Best Microscopic Ear Surgery Specialist in Bavdhan , Kothrud,Pune and PCMC Best Microscopic Ear Surgery Specialist in Pune and PCMC Dr Aniruddha Phadke – Dr Phadke’s ENT & Rhinoplasty Clinic When it comes to advanced and... View service → |
What should you avoid while waiting for an appointment?
Do not put cotton buds, hairpins or any other object into the ear. They can push wax deeper, cause ear damage, scratch the canal or perforate the eardrum. Stop home cleaning if wax will not come out easily.
- Avoid oil and leftover ear drops, including antibiotic or steroid drops. Antibiotics do not treat every ear problem, and the eardrum must be checked before certain drops are used, especially after ear surgery or when perforation is possible.
- Finish prescribed treatment exactly as directed. Less pain does not prove that the infection or underlying problem has resolved.
- Arrange professional earwax removal when home removal is unsafe, a perforation is known or suspected, or hearing loss remains after wax removal. Repeated instrumentation can worsen blockage and injury.
Painless ear discharge still needs attention if it persists, returns through a perforation or smells foul. Ongoing drainage can damage hearing even without severe pain. If you have diabetes or immune suppression, seek prompt review for severe pain out of proportion to the examination, granulation tissue or continuing drainage.
Go to urgent care for sudden hearing loss, facial weakness, swelling behind the ear, severe vertigo, high fever, blood or clear fluid from the ear.
Frequently asked questions
How long can you wait before persistent ear symptoms need assessment?
Arrange medical review when ear pain, blocked hearing, fullness, itching or discharge continues beyond 48 to 72 hours without clear improvement. Ongoing drainage after treatment or drainage that returns through a perforated eardrum also needs assessment.
What can repeated ear episodes, one-sided symptoms and lasting fluid indicate?
They can point to an underlying problem that needs examination rather than repeated self-treatment. An ENT specialist can check the eardrum, middle ear, ear canal and hearing to identify the cause.
Which symptom patterns point beyond an ordinary ear infection?
Seek evaluation for recurring episodes, symptoms confined to one ear, persistent fluid or hearing loss, continuing discharge, severe dizziness, facial weakness or worsening pain.
What happens during an ENT evaluation?
The clinician reviews your symptoms and treatments, examines the ear canal and eardrum, and checks hearing when needed. Bring a list of medicines, previous diagnoses, treatment dates and details about discharge or hearing changes.
What should you avoid while waiting for an appointment?
Do not insert cotton buds or other objects, flush the ear, scratch the canal or use leftover ear drops. Keep the ear dry and seek urgent care for severe dizziness, facial weakness or rapidly worsening symptoms.